Every medication has a story. Ketamine’s is longer than most.
It took six decades of research, clinical use, and unexpected discovery to bring this drug to where it stands today — in the hands of board-certified anesthetists, treating some of the most complex conditions in medicine.
If you are sitting with years of failed treatments behind you, that history matters. Understanding where ketamine came from helps explain why it may help when so many other things have not.
This is that story.
1962: A Drug Is Born in a Detroit Laboratory
Ketamine was first synthesized in 1962 by chemist Calvin Stevens at Parke-Davis Pharmaceuticals. The goal was practical and urgent.
Researchers were looking for a safer alternative to phencyclidine (PCP). PCP was an effective anesthetic — but its side effects made it dangerous. Stevens’ new compound worked differently.
It produced rapid sedation. It preserved breathing. It was chemically stable. Those qualities made it immediately interesting to medicine.
The drug had a name: CI-581. The world would come to know it as ketamine.
1964 to 1970: From Laboratory to Battlefield

The first human trials began in 1964. The results were promising. Researchers at the University of Michigan Medical Center confirmed what the lab had suggested.
Ketamine worked as a dissociative anesthetic. Patients under its effect were sedated but maintained their own airway. That was a significant safety advantage.
The FDA approved ketamine in 1970 as a human anesthetic. Its first major deployment was not in a hospital. It was in Vietnam.
Military medics administered it to wounded soldiers in the field. It required no ventilator, no complex equipment. A medic could administer it and the patient would remain stable.
Its combat record saved lives. That history shapes how ketamine is understood to this day.
1970s and 1980s: Broad Clinical Use

After FDA approval, ketamine moved into mainstream medicine. Anesthesiologists used it in emergency settings, pediatric procedures, and situations where preserving airway reflexes was critical.
Jenice Hughes, CRNA, has been administering ketamine for 25 years. Her career spans an era when ketamine was already a well-understood clinical tool — not an experiment, but an established medication with a documented safety profile.
That depth of hands-on experience is not common. Most ketamine clinics in operation today are measured in years. Jenice’s clinical relationship with this medication spans a quarter century.
During this period, ketamine also entered the veterinary world. Its use as an animal anesthetic is part of why some people associate it with a non-medical context. The clinical reality is different.
1990s: The First Clues About Mental Health
The 1990s brought something no one had anticipated. Researchers began noticing that ketamine’s mechanism of action was unlike any psychiatric medication on the market.
Most antidepressants at the time worked on serotonin or norepinephrine — the neurotransmitters targeted by SSRIs and SNRIs. Ketamine did something different.
It blocked a receptor called the NMDA receptor (N-methyl-D-aspartate receptor). That receptor is involved in glutamate signaling — a different neurochemical pathway entirely.
Glutamate is the brain’s primary excitatory neurotransmitter. In depression and PTSD, glutamate dysregulation appears to play a significant role. SSRIs do not address this pathway. Ketamine does.
Early research suggested ketamine’s effect on glutamate could explain rapid mood changes some patients reported following anesthetic doses. That observation opened a door.
2000: The Landmark Study That Changed Everything
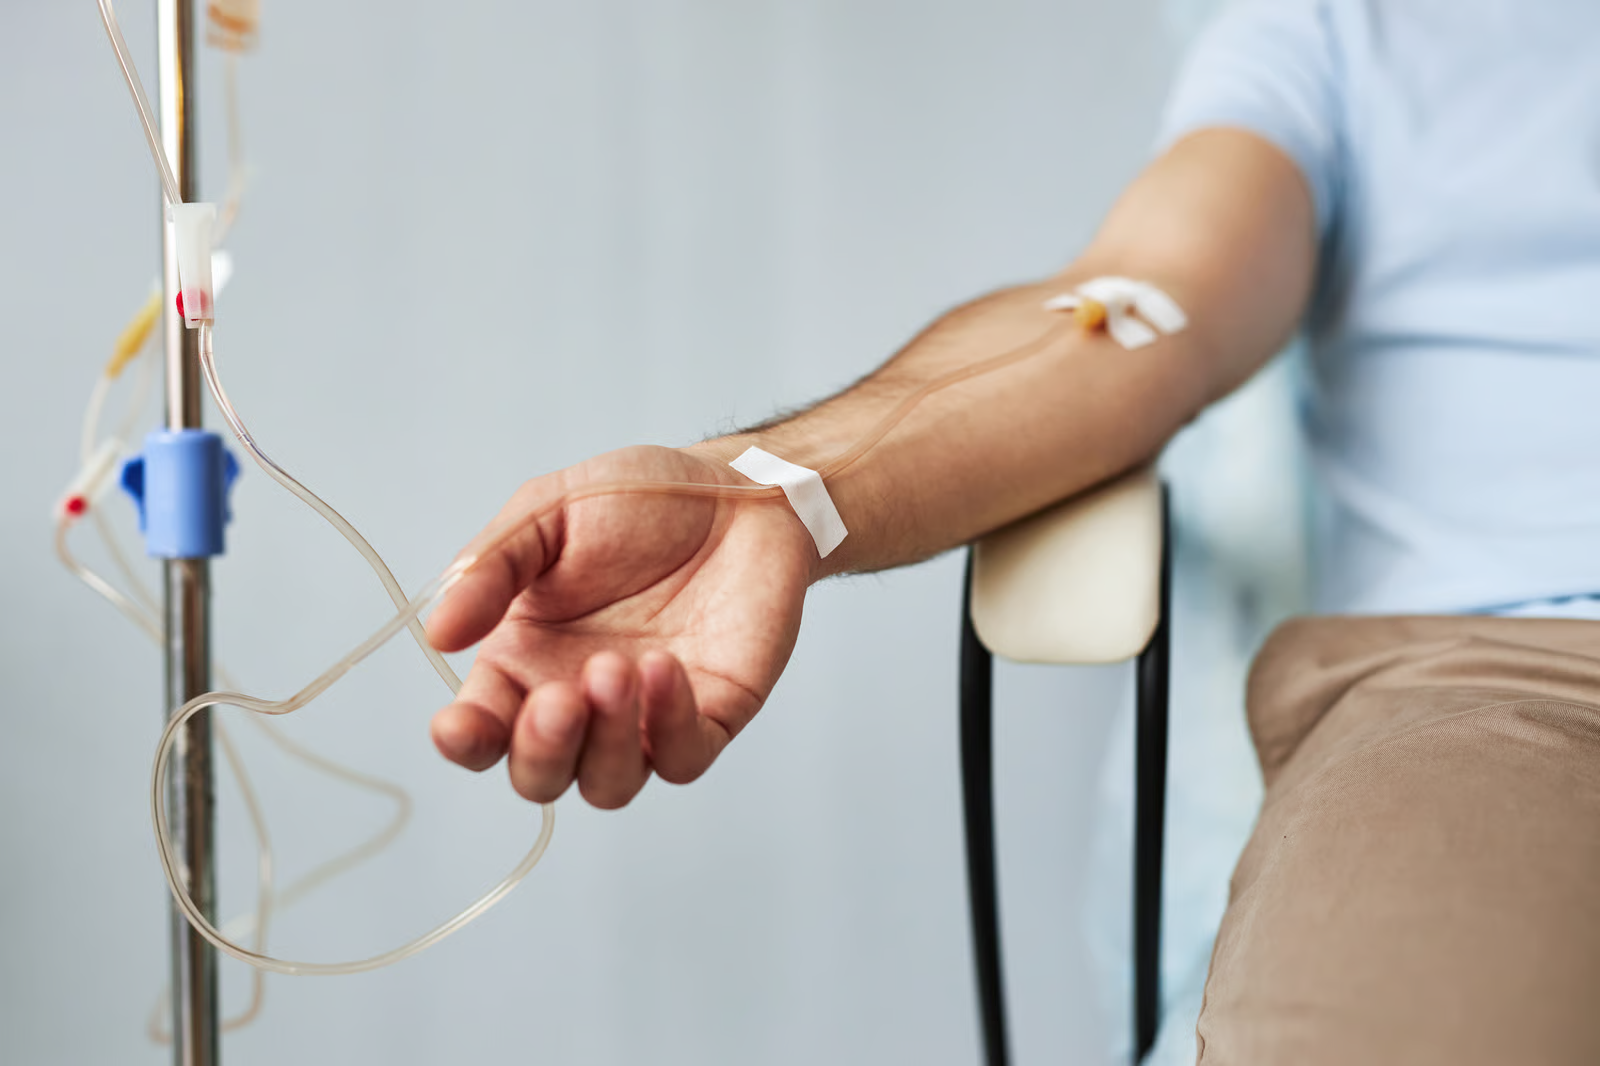
In 2000, researchers at the National Institute of Mental Health (NIMH) published a small but significant study. Patients with treatment-resistant depression received a single sub-anesthetic dose of IV ketamine.
The results were striking. Many participants reported substantial improvement in depressive symptoms — within hours, not weeks.
Read the original NIMH study overview at the National Institute of Mental Health.
This was unlike anything the field had seen. Traditional antidepressants require two to four weeks before a patient notices any change. Ketamine’s response, for some patients, was measured in hours.
That speed matters enormously for a patient in crisis. For a patient who has tried three antidepressants without relief, it also represented a different biological mechanism — one that might reach what other medications could not.
2006 to 2012: Replication and Growing Evidence
The NIMH finding was replicated. Then replicated again.
Researchers at Yale, Oxford, and institutions across the US and Europe began publishing studies on IV ketamine for depression, PTSD, anxiety, and chronic pain. The evidence base grew carefully.
Explore Yale’s published research on ketamine and depression at Yale Medicine.
Key findings across this period included:
-
Rapid antidepressant effects observed in patients who had failed multiple prior treatments
-
NMDA receptor antagonism as a plausible neurobiological mechanism
-
Neuroplasticity effects: ketamine appeared to promote the growth of new synaptic connections in brain regions affected by depression
-
Pain modulation: the same receptor blockade that affected mood also interrupted certain chronic pain signaling pathways
-
PTSD applications: early studies suggested ketamine may reduce the intensity of traumatic memory consolidation
This was not fringe research. It was peer-reviewed, replicated, and published in leading journals.
2019: FDA Approval for Treatment-Resistant Depression
The most important regulatory milestone in ketamine’s psychiatric history arrived in March 2019.
The FDA approved esketamine (Spravato) — a nasal spray form of a ketamine compound — for treatment-resistant depression in adults who had failed at least two antidepressant treatments.
This approval was significant for several reasons. It confirmed that the FDA recognized the clinical evidence for ketamine-related compounds in treatment-resistant depression. It validated two decades of research.
IV ketamine itself remains used off-label for mental health and chronic pain conditions. “Off-label” does not mean experimental or unproven. It means the FDA has not completed the specific approval process for that delivery method.
IV ketamine has a well-established safety record, extensive clinical literature, and decades of monitored use. The distinction between IV ketamine and Spravato is one of regulatory pathway, not clinical legitimacy.
2020 to Now: Ketamine in a New Era
The last five years have brought a significant expansion of ketamine therapy access. That growth has been uneven.
Telehealth companies now offer at-home ketamine prescriptions with minimal clinical oversight. Some operate with ethical rigor. Others do not. The proliferation of providers has made it harder for patients to know what they are choosing.
LegitScript certification was developed in part to address this problem. Scottsdale Ketamine Clinic is LegitScript certified — an independent verification of clinical legitimacy, regulatory compliance, and ethical advertising standards.
Learn more about LegitScript certification and what it requires at LegitScript.com.
In a ketamine landscape that has grown rapidly and unevenly, that certification marks a real distinction.
Sixty Years Later: What It Means for You
Ketamine was not designed to treat depression. It was not designed to help someone with PTSD finally sleep through the night. It was not designed to reduce the crushing daily pain of CRPS or fibromyalgia.
It was designed to keep a wounded soldier stable on a battlefield.
What happened over the sixty years that followed was the slow accumulation of clinical evidence pointing toward something unexpected. A medication that belonged to anesthesia turned out to have properties that standard psychiatry could not replicate.
That is the story a patient inherits when they walk into Scottsdale Ketamine Clinic.
They are not stepping into something experimental. They are stepping into the current chapter of a sixty-year clinical history — administered by a CRNA who has spent 25 of those years working with this medication directly.
If you have been through multiple treatments without adequate relief, this history may be relevant to your next step.
We offer a free consultation at both our Scottsdale and Phoenix locations. There is no obligation. It is simply a conversation about whether ketamine may be appropriate for your situation.
Call our Scottsdale clinic: 480-613-3226, Call our Phoenix clinic: 480-590-6154, Or complete the consultation request form on our website.
Medical Disclaimer: This article is for informational purposes only and does not constitute medical advice. Please consult a qualified medical professional before beginning any treatment. Ketamine therapy may not be appropriate for all individuals.
Crisis Resource: If you or someone you know is in crisis, call or text 988 to reach the Suicide and Crisis Lifeline. Ketamine therapy is not an emergency intervention.